01 / The central distinction
Pain relief and tissue repair are separate endpoints.
Cooling may reduce pain and change local temperature or circulation. Whether it accelerates tissue regeneration or improves return to activity is a separate question. Human evidence does not establish all these outcomes as equivalent benefits.[1]
Claims that ice invariably stops healing also exceed the evidence. Concerns about regeneration rely substantially on animal and laboratory studies whose injury types, tissue depths and cooling protocols differ from brief cooling of human injuries.
Pain, regeneration and recovery endpoints
Pain now
Cooling can reduce pain and alter nerve conduction. Relief is a symptom outcome.
Repair biology
Animal and laboratory studies examine inflammation, blood flow and regeneration. Transfer to human injuries is uncertain.
Recovery later
Function, return to activity and reinjury need human follow-up. Less pain does not prove faster healing.
02 / What changes under a cold pack
Cooling acts on several processes at once.
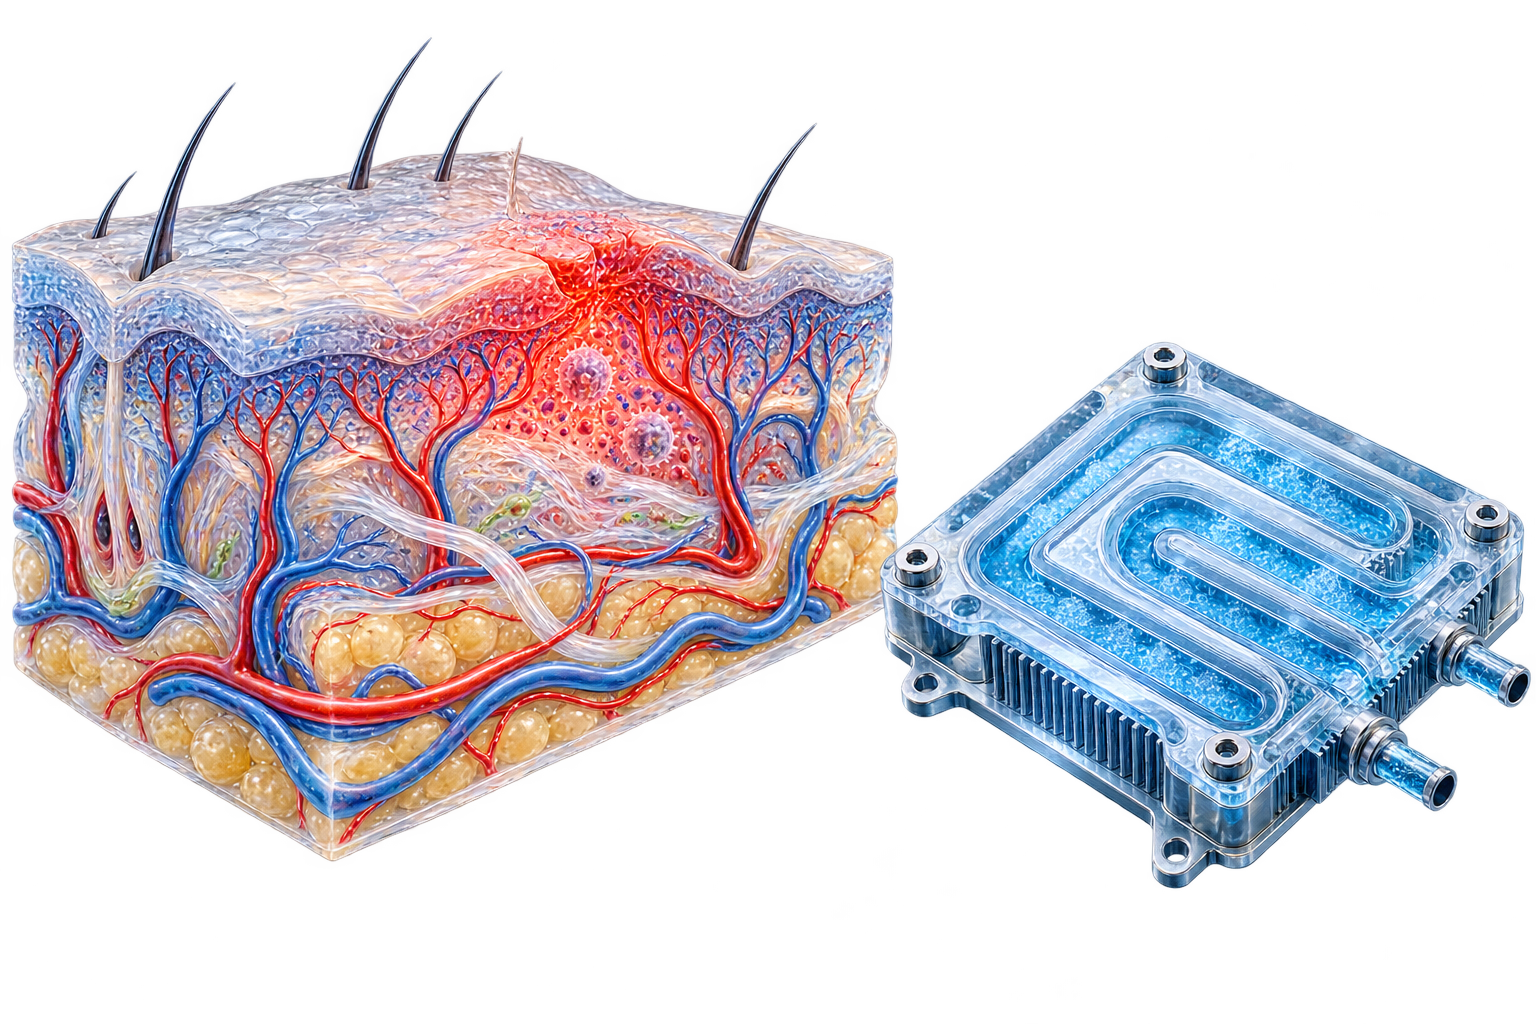
Cooling can reduce nerve conduction, alter pain perception, constrict local vessels and reduce metabolic activity. Cooling at depth depends on tissue, blood flow, method and duration. Skin temperature does not establish the temperature at the injury.
Immune cells clear damaged tissue and coordinate repair. Strong or prolonged cooling could therefore affect regeneration, but biological plausibility does not quantify clinical harm. The net effect requires testing in the relevant human injury and exposure context.
A 2024 critical review found analgesic effects but no human evidence establishing that cryotherapy limits secondary injury or improves tissue regeneration. It also stressed the limits of translating animal muscle-injury experiments to human sport injuries. This is a statement about missing evidence for particular benefits, not proof that every clinical use is harmful.[1]
03 / Trial comparisons
The comparator determines the trial’s scope.
In a randomized study of acute ankle sprains, Bleakley and colleagues compared two icing protocols. Intermittent application reduced pain during activity at one week compared with the standard protocol. The groups did not differ significantly on several other outcomes, including function, swelling and pain at rest. Both groups received ice: this design cannot establish the benefit of ice over no ice.[2]
A comparison of two cooling schedules cannot establish whether cooling is necessary. Postoperative findings may not apply to fresh muscle tears, and early pain differences do not establish lower reinjury rates months later.
Reasonable inference
Some cooling protocols may help short-term pain in particular injuries.
Unsupported leap
Therefore every injured tissue heals faster when cooled, or every inflammatory response benefits from suppression.
04 / Skin and sensory limits
Cooling changes sensation as well as pain
Cooling can injure skin. Circulation and sensory disorders alter tissue response and exposure to that risk. Numbness reduces sensory feedback, while pain relief can occur before structural recovery. Neither sensation alone establishes tissue integrity or readiness for loading.[3]
Swelling, deformity, inability to bear weight and pain intensity are observations with multiple possible causes. A cold pack cannot distinguish a fracture from a soft-tissue injury.
Sources & further reading
Follow the evidence.
- 01Racinais et al. (2024): Cryotherapy for Treating Soft-Tissue Injuries
Critical review separating analgesia from uncertain regeneration effects.
- 02Bleakley et al. (2006): Two Icing Protocols for Acute Ankle Sprains
Randomized protocol comparison; no untreated control group.
- 03NHS: Sprains and Strains
Public information on sprains, strains and cooling.