01 / Responses and diagnostic limits
Protective responses have multiple causes.
Coughing, sneezing and fever often accompany respiratory illness, but they are different processes. A cough helps move material out of the airways. A sneeze responds to irritation in the nose and nearby tissues. Fever is a regulated rise in body temperature associated with immune and inflammatory signaling. None, by itself, identifies a particular germ or quantifies immune control.[1][2][3]
Symptoms have multiple possible causes.
Trace a response
Detect
Airway sensory nerves respond to irritants and other triggers.
Coordinate
Brainstem circuits organize breathing muscles and the larynx.
Expel
Airflow can remove material; repeated coughing may outlast an infection.
02 / Airway expulsion
Cough and sneeze use different sensory routes.
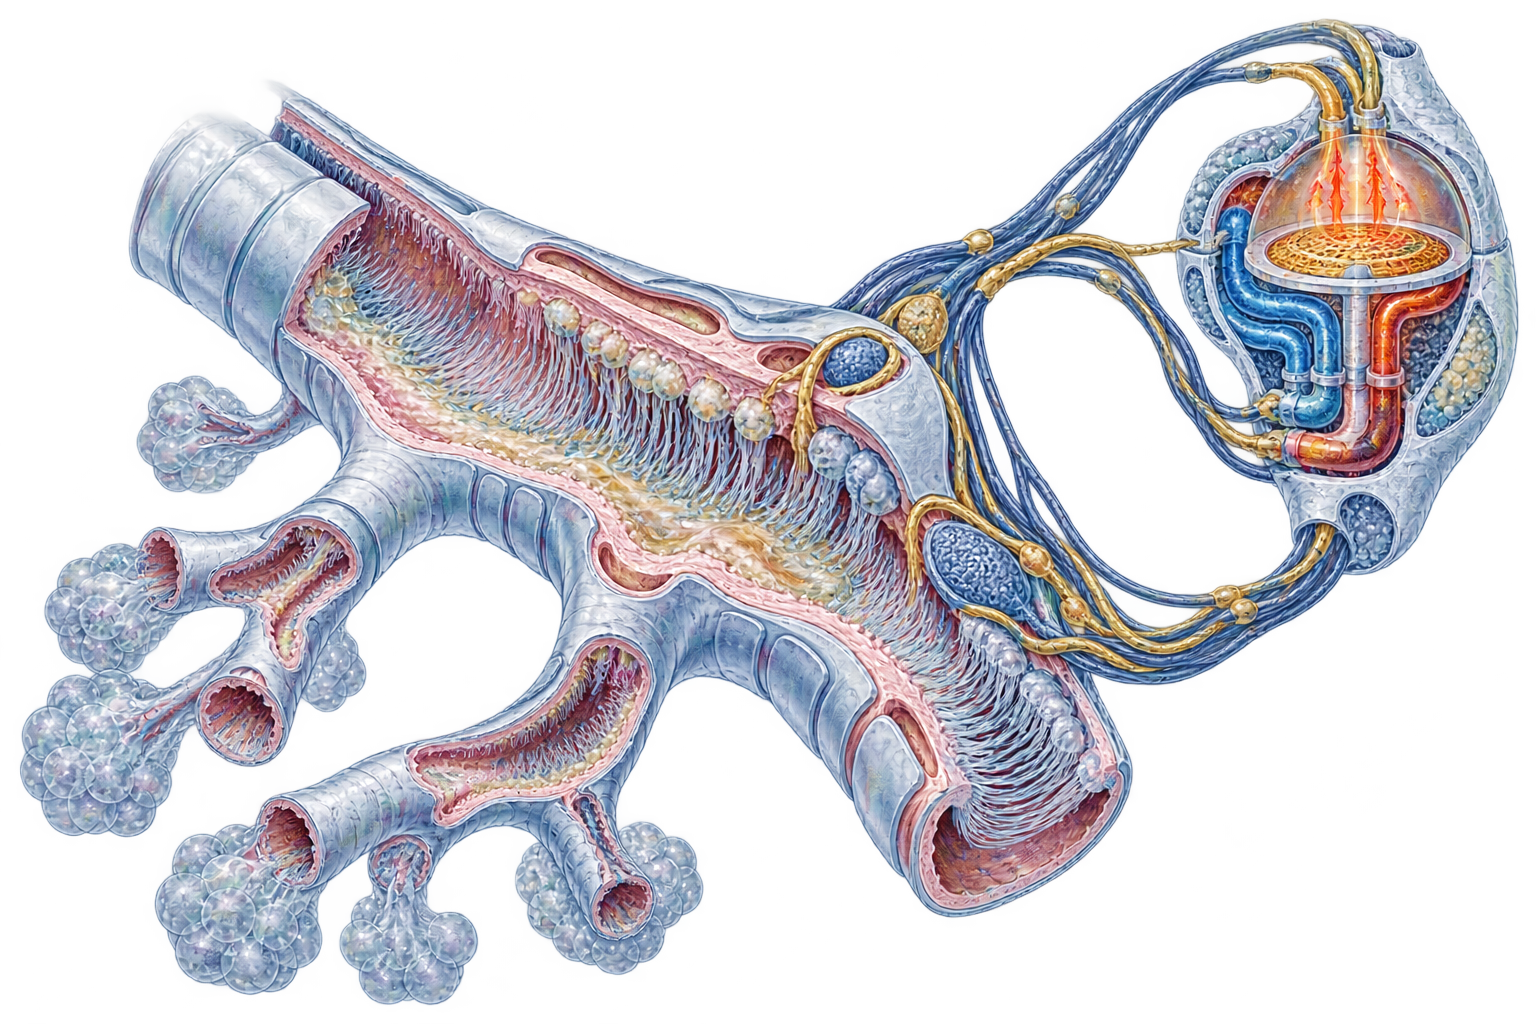
Airway sensory nerves detect chemical and mechanical triggers. A cough coordinates breathing muscles and the larynx to create an expulsive airflow. Mucus production and ciliary movement also help maintain airway clearance. A cough may be productive or dry; its presence does not mean that every cough is successfully removing an infection.[1]
Infections are only one cause. Asthma, reflux, smoking, environmental irritants and some medicines can cause coughing. Airways may remain sensitive after an acute infection has passed. Duration and associated symptoms can therefore matter more than the assumption that “a lingering cough means living bacteria are still there.”
Sneezing usually begins with irritation of nasal mucosa and sensory pathways including the trigeminal nerve. Allergens, dust and infections can all trigger it. The coordinated burst of air can expel material, but it also distributes respiratory particles. Neither the force nor the number of sneezes measures the strength of someone’s immune system.[2]
Watery eyes and sneezing can occur with allergy or infection. The mechanism alone cannot distinguish the cause in an individual.
03 / A changed regulated temperature
Chills during a rising fever
During fever, inflammatory signals influence prostaglandin pathways and temperature regulation in the brain. If the regulated level rises above the current temperature, the body can conserve and generate heat through skin-vessel constriction and shivering. A person may feel cold while a thermometer is moving upward. When the regulated level falls again, heat loss and sweating can follow.[3]
This differs from hyperthermia, in which heat production or environmental heat overwhelms cooling without the same regulated set-point change. Heatstroke is severe hyperthermia, not an ordinary regulated fever. A temperature number does not encode its cause.
Temperature also varies with measurement site, time of day and activity. A high fever is not a precise ranking of infection severity, and serious illness can occur without a striking fever. Age and immune status also change the distribution of temperature responses.
Mechanism
A raised regulated temperature can be part of a host response to illness.
Inference limit
That role does not imply that every fever is harmless or that relief inevitably impairs recovery.
04 / Context limits inference
Symptoms do not reveal a single cause.
Respiratory particles can leave the tract during coughing, sneezing and ordinary exhalation. Shared indoor air therefore contributes to transmission even when a person is not coughing. Symptom suppression does not establish absence of infectiousness.[4]
Limits of the mechanism map
The response map identifies biological sequences. The same cough or fever mechanism can occur under different causes, and the map does not rank severity or predict outcomes for an individual.
Sources & further reading
Follow the evidence.
- 01
- 02
- 03
- 04